Introduction
You are fine one moment. Then a tone of voice, a smell, a date on the calendar or a message that lands the wrong way arrives, and within seconds your heart is racing, your thoughts are spinning, or you have gone numb. Afterward you may wonder why something that looked small from the outside produced such a big reaction.
This experience is common, and it is rarely random. The World Health Organization (WHO) estimates that nearly 1 in 7 people worldwide, about 1.1 billion, were living with a mental disorder in 2021, and the WHO defines mental disorders in part by disturbances in thinking, emotional regulation or behavior. Strong, hard-to-control emotional reactions are not a niche problem. They run through everyday life, relationships, workplaces, and nearly every clinical condition.
This guide explains what emotional triggers are, why they happen, and what the research says about managing them. It covers quick tools you can use in the moment, habits that lower your reactivity over time, professional treatments, and how clinicians can work with triggers safely. Some sections speak mainly to general readers and some mainly to professionals, but all of it is written to be readable by both.
1. What Is an Emotional Trigger?
In everyday speech, “triggered” has become a catch-all for anything that irritates or upsets us. In psychology, the idea is narrower and more useful.
An emotional trigger is a cue, external or internal, that sets off a strong emotional, physical or behavioral reaction because the mind has linked it with earlier experience. That experience is usually painful, threatening or unresolved. The cue can be a sight, sound, smell, place, person, phrase, body sensation or even a thought. The reaction can show up as anxiety, anger, shame, sadness, panic, urges to escape or lash out, or numbness and shutdown.
Three points are worth holding onto:
- A trigger is not the same as a cause. The cue activates a response that was already learned. The “real” source lies in the history and the associations, not in the cue itself.
- Triggers are personal. What is neutral to one person can be intensely distressing to another, depending on their experiences, culture, and current state.
- Being triggered is not a character flaw or a diagnosis. It is a sign that your nervous system is doing what it learned to do, often to protect you.
The term has deep roots in trauma research. The U.S. Substance Abuse and Mental Health Services Administration (SAMHSA) describes trauma through three “Es”: the event or events, the person’s experience of them, and the lasting effects. Guidance built on that framework notes that reminders such as sights, sounds, smells or thoughts can trigger reactions, and that triggers differ for each person. Over time, the word spread beyond clinical settings. That is not a problem in itself, but it helps to keep the original meaning in mind: a trigger is a learned link between a cue and a reaction.
2. Why Triggers Happen
The brain learns associations quickly
The brain is built to link cues with outcomes. If a cue once appeared alongside danger, humiliation or loss, the brain can respond to that cue later as if the danger were present again. This is fast and automatic, and it often happens before we have time to think. That is why people frequently say, “I knew it wasn’t logical, but I couldn’t stop it.”
A useful, simplified picture has two systems. A fast alarm system, in which the amygdala plays a major role, flags possible threats within moments. A slower reflective system, supported by regions of the prefrontal cortex, helps us interpret, weigh and choose. Many regulation skills work by engaging the second system so that it can steady the first. One neuroimaging study found that putting feelings into words reduced amygdala responses to emotional images and increased activity in a region of the right prefrontal cortex. The finding comes from a controlled laboratory setting, so it is best read as supporting evidence for a mechanism rather than a guarantee for every situation.
Memory can reactivate without the story
Emotional memories are stored with sensory and bodily detail. A cue can bring back the feeling, the body state or the urge without bringing back a clear narrative of what happened. This helps explain why triggers can seem to come from nowhere, and why people sometimes cannot say what upset them until later.
Meaning and context matter
The same cue can land very differently depending on how we interpret it and what state we are in. A short reply to a message may be neutral on a rested day and feel like rejection after poor sleep, a conflict, or a stressful week. Sleep loss, hunger, illness, alcohol, overwork and accumulated stress all lower the threshold for a reaction. Think of reactivity as the product of the cue, your history, and your current load.
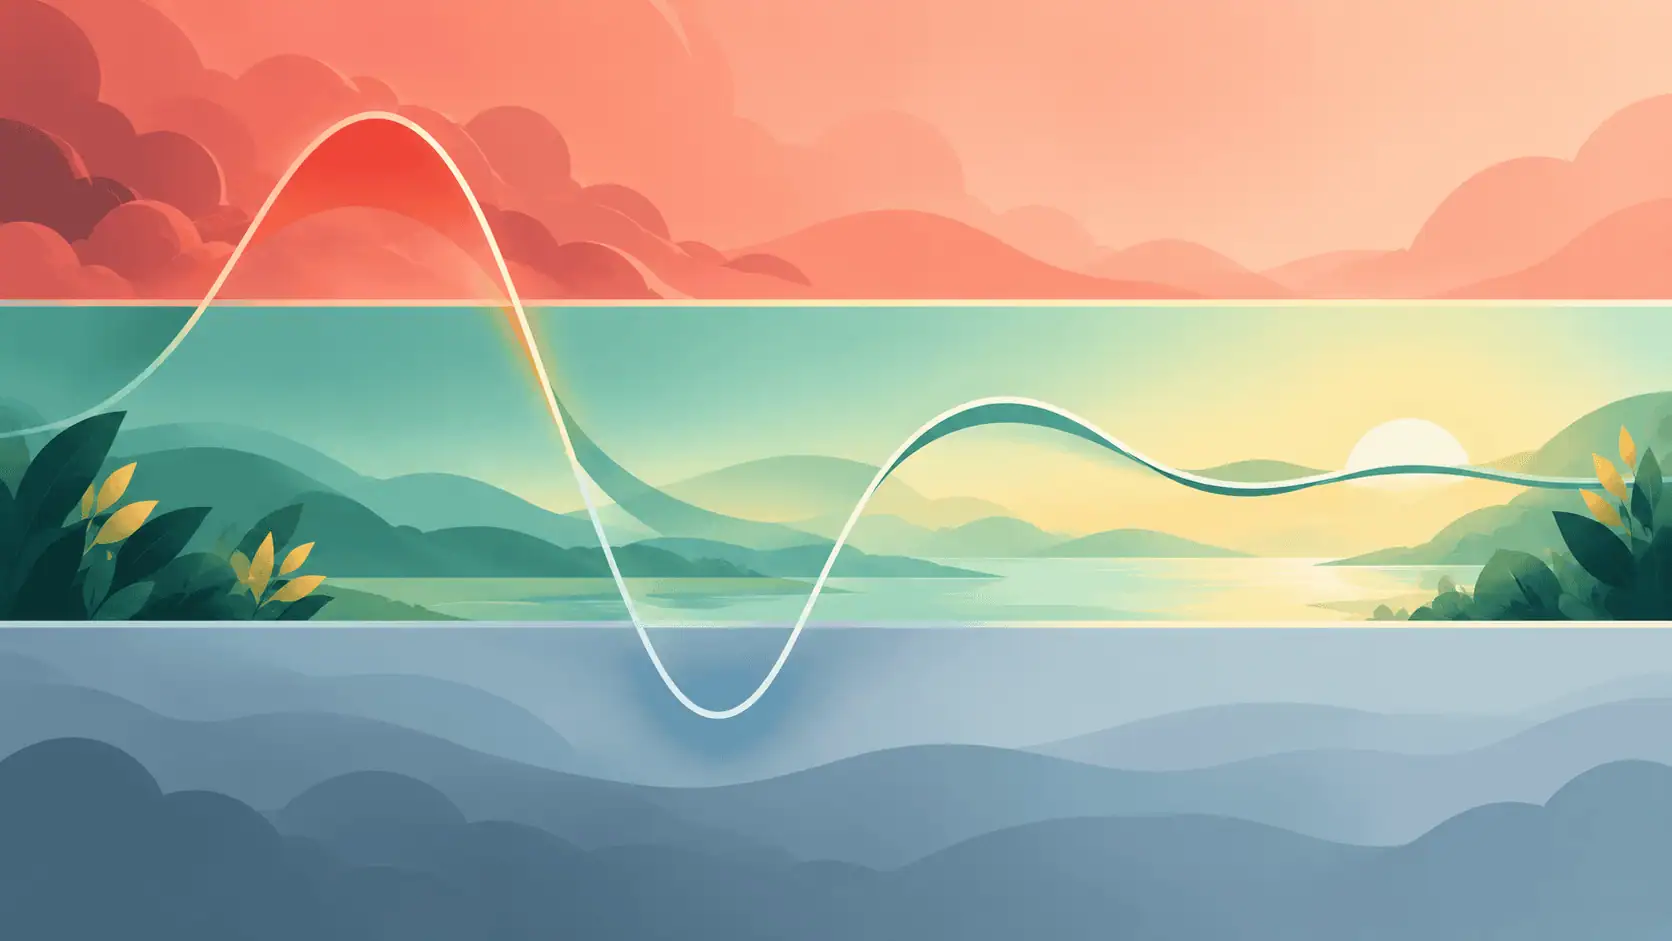
The window of tolerance
Psychiatrist Dan Siegel’s concept of the window of tolerance is a popular clinical map for this. It describes the zone of arousal in which a person can feel emotions, think clearly and respond flexibly. Triggers can push people out of that window in one of two directions:
- Above the window (hyperarousal): panic, anxiety, anger, racing thoughts, feeling flooded, or an urge to fight or flee.
- Below the window (hypoarousal): numbness, emptiness, fatigue, blankness, disconnection or dissociation.
The window is a metaphor, not a measured structure, but it is practical. It reminds us that the goal of regulation is rarely to feel nothing. The goal is to return to a range where we can think, choose and stay connected, and over time to widen that range.
3. Common Types of Triggers
Triggers tend to fall into a few broad families. Naming yours is the first step toward managing them.
- Sensory triggers: smells, sounds, textures, tastes, lighting, places or anniversaries linked to a painful time.
- Interpersonal triggers: criticism, being ignored or excluded, feeling controlled, raised voices, perceived disrespect, cues of abandonment, or unpredictability in a close relationship.
- Situational triggers: crowded or enclosed spaces, medical settings, authority figures, performance evaluations, conflict, endings and transitions.
- Internal triggers: body sensations such as a racing heart, self-critical thoughts, memories, intense emotions themselves, hunger or exhaustion.
- Media and collective triggers: news, social media, public events, discrimination and microaggressions, or reminders of shared community pain.
- Role-based triggers: caregiving demands, parenting, workplace hierarchy, or being in a position of dependence.
Many people find that one trigger rarely acts alone. A critical comment (interpersonal) on a day without sleep (internal) in a noisy room (sensory) is far more likely to tip someone out of their window than any single factor.
4. Triggers, Trauma and Clinical Conditions
This section is written mainly for professionals but is useful for anyone who wants more precision.
Everyday emotional reactivity versus trauma-related re-experiencing. Many triggers involve strong feelings tied to past hurts, but they stay anchored in the present: the person knows where they are and can usually recover. Trauma-related triggering can go further, with intrusive memories, flashbacks, nightmares, a sense that the threat is happening now, and strong avoidance. In the WHO’s ICD-11, post-traumatic stress disorder (PTSD) centers on re-experiencing in the here and now, avoidance of reminders, and a persistent sense of current threat. Complex PTSD adds disturbances in self-organization, including difficulties with emotion regulation, negative self-concept and relationships.
Triggers appear across diagnoses. They are not limited to trauma-related conditions:
- In panic and anxiety disorders, internal cues such as a fast heartbeat or dizziness can set off fear of fear.
- In depression, reminders of loss or perceived failure can start rumination spirals.
- In borderline personality disorder and related presentations, interpersonal cues such as perceived rejection can trigger rapid, intense shifts in emotion.
- In substance use and eating disorders, people, places, moods and sensations can trigger cravings, urges to restrict or binge, or compensatory behaviors.
- In bipolar disorder, sleep disruption and high stress can trigger mood episodes, so it matters to distinguish triggers of emotions from triggers of illness episodes.
- In OCD, intrusive thoughts or contamination cues trigger obsessions and compulsions.
- In neurodivergent people, sensory overload and unpredictability can produce reactions that look like emotional triggering but may call for environmental accommodation as much as emotional skills.
Assessment pointers. When a client says “I’m triggered,” clarify what they mean: the cue, the reaction, how long it lasts, how quickly they recover, and what they do next. Consider dissociation, psychosis, substance effects, medical contributors (for example thyroid problems or medication side effects), and risk. Validated measures such as the Difficulties in Emotion Regulation Scale (DERS) for regulation difficulties or the PTSD Checklist for DSM-5 (PCL-5) for trauma symptoms can help track change, alongside a good clinical interview.
5. Mapping Your Own Triggers
You cannot manage what you cannot see. A few weeks of simple tracking often reveals patterns that feel invisible in the heat of the moment.
A simple trigger log
When you notice a strong reaction, jot down, as soon as you can:
- Situation: what was happening, who was there, what time it was.
- Body signals: tight chest, hot face, nausea, heaviness, shaking, numbness.
- Thoughts: what went through your mind, in your own words.
- Emotion and intensity: name it and rate it from 0 to 10.
- Urge and action: what you wanted to do and what you did.
- What helped or made it worse.
- Possible link: does this remind you of anything from before?
What to look for
- Early warning signs. Reactions usually build. Learn your first signals, such as a clenched jaw, shallow breathing, irritability or going quiet. The earlier you catch them, the more options you have.
- Hot times and conditions. Many people find reactivity rises when they are hungry, angry, lonely or tired. A common clinical shorthand for this is HALT.
- Themes. Triggers often cluster around a few core themes, such as feeling unsafe, unseen, judged, controlled, abandoned or powerless.
A caution for trauma survivors
If you have lived through trauma, keep the log focused on present-day cues and reactions. You do not need to write out the details of what happened. If tracking itself becomes overwhelming, stop and take it to a therapist. Professionals can help you map triggers in a paced, safe way.

6. In-the-Moment Strategies
When you are triggered, the aim is to come back inside your window of tolerance, not to force the feeling away. The steps below can be used in order or picked individually. Practice them when you are calm, because skills are much harder to find in a crisis if you have never used them before.
Step 1: Pause and name what is happening
Silently say something like, “I’m being triggered,” or “This is anxiety.” Naming a feeling creates a small gap between you and the reaction. Neuroimaging research on affect labeling, such as the study published in Psychological Science, suggests this simple act can reduce emotional reactivity. Be as specific as you can: “irritated and a bit ashamed” is more useful than “bad.”
Step 2: Ground yourself
Grounding brings attention out of the spiral and into the present. The WHO’s illustrated self-help guide, Doing What Matters in Times of Stress, teaches a grounding exercise in three moves: notice your thoughts and feelings, slow down and connect with your body (for example by pressing your feet into the floor, stretching and breathing), then refocus and engage with what is around you and what you are doing. The guide was field-tested for people in many circumstances and is available in several languages.
A common variation is “5-4-3-2-1”: name five things you can see, four you can feel, three you can hear, two you can smell and one you can taste. Use whatever version keeps your attention in the room.
Step 3: Slow your breathing, if breath focus feels safe
Breathing out a little longer than you breathe in can help settle the body. Try breathing in for about four counts and out for about six. A small number of people find that focusing on the breath increases anxiety, especially if they have panic or trauma histories. If that is you, skip it and use movement, touch, or your senses instead.
Step 4: Use your body
Simple movement can shift your state: walking, stretching, shaking out your hands, rolling your shoulders, pressing your palms together, or a warm shower. If you are in the hypoarousal range (numb, foggy, frozen), gentle activating actions such as standing up, moving around, or noticing textures and sounds can help more than calming exercises.
Step 5: Create space
If you can, step away. Leave the room, go outside for a few minutes, or say, “I need a few minutes, and I’ll come back to this.” Delay important replies, especially written ones. A “one night before sending” rule prevents many regretted messages.
Step 6: Reappraise, once you are steadier
When the intensity has dropped, ask: What else could this mean? What would I say to a friend in this situation? What is the evidence for and against my first interpretation? Reappraisal works best after the initial surge. Trying to argue with a thought at peak intensity usually backfires.
Step 7: Reach out
Contact someone safe, even briefly. You do not need to explain everything. “I’m having a hard moment, can I talk for five minutes?” is enough.
Step 8: Be kind to yourself afterward
Shame often follows a strong reaction and makes the next trigger worse. Treat it the way you would treat a friend: acknowledge that it was hard, note what helped, and rest.
What tends to make things worse
- Suppressing or hiding the feeling. Research on emotion regulation finds that suppression reduces outward expression but does not reduce the felt emotion, and it increases physiological arousal.
- Alcohol and other substances, which may dull things briefly but disrupt sleep, mood and judgment.
- Rumination and doomscrolling, which keep the alarm system activated.
- Sending the message, firing the email, or making the big decision in the heat of the moment.
7. Building Resilience Between Triggers
In-the-moment skills help you get through. Daily habits determine how easily you are triggered in the first place.
Understand the difference between reappraisal and suppression
James Gross’s process model of emotion regulation proposes that we can influence emotions at several points: choosing or changing situations, directing attention, changing how we interpret events, and modulating our responses. His review found that reappraisal, which changes how a situation is construed, reduces emotional experience without a memory cost, while suppression does not reduce experience and impairs memory. The practical lesson is to work earlier in the chain where possible: notice, reframe and plan rather than clamp down.
Reappraisal has limits. It is not a way of talking yourself out of a situation that is truly unsafe, unfair or harmful. When the problem is real, the better move is often to change the situation, set a boundary or seek help.
Practice mindfulness and acceptance, adapted to you
A large systematic review and meta-analysis in JAMA Internal Medicine found moderate evidence that mindfulness meditation programs improve anxiety, depression and pain, with small to moderate effects, and no evidence that they outperform other active treatments. So mindfulness is a reasonable tool, not a cure-all. Some trauma survivors find silent, inward-focused practice distressing. If that is you, try shorter practices with eyes open, movement-based approaches, or guidance from a trauma-informed instructor.
The WHO guide mentioned earlier also teaches “unhooking” from difficult thoughts, “making room” for hard feelings, acting on your values, and being kind to yourself. These are drawn from acceptance-based approaches and can be practiced in a few minutes a day.
Lower your baseline load
- Sleep: protect it. It is one of the biggest levers on emotional reactivity.
- Food, movement and light: regular meals, daily physical activity and time outdoors support mood and stress tolerance.
- Alcohol and caffeine: notice how they affect your anxiety and sleep.
- Workload and rest: schedule recovery before you hit your limit.
Set boundaries and communicate clearly
Many triggers are relational. Learn to name needs without blame: “When voices get raised, I shut down. I’d like to pause and continue in ten minutes.” Agreeing on pause signals with partners, family or colleagues can prevent escalation. Boundaries are not punishments; they are information about what helps you stay in your window.
Strengthen support
Connection is protective. That can include friends, family, community, faith groups, peer support groups and professionals. SAMHSA’s trauma-informed principles include peer support and mutuality as core elements because people often recover better alongside others who understand.
Practice when you are calm
The WHO guide suggests building skills during ordinary moments, such as a minute while waiting or after a daily routine, so they are easier to reach during hard ones. A few minutes of daily practice usually beats an occasional long session.

8. Professional Treatment
When self-help is not enough
Consider professional support if triggers regularly disrupt your sleep, work, study or relationships, if you avoid more and more places or people, if you use alcohol, drugs or self-harm to cope, if you have flashbacks or nightmares, or if you feel numb or disconnected much of the time. Needing help is not a sign that you have failed. It is a sensible response to a problem that has become bigger than self-management.
What the guidelines say about trauma-related triggers
For PTSD, WHO guidance recommends trauma-focused cognitive behavioral therapy (CBT-T), eye movement desensitization and reprocessing (EMDR), and stress management as treatment options. The WHO’s updated mhGAP guideline similarly lists individual or group CBT with a trauma focus, digital CBT with a trauma focus, EMDR and stress management, noting that the best choice depends on resources and personal preference. It also notes that group CBT with a trauma focus and EMDR are more effective than stress management, while stress management may be the more feasible option where resources are limited, and that EMDR and trauma-focused CBT can include complex techniques that call for properly trained and supervised providers.
Skills-based and other therapies
- Dialectical behavior therapy (DBT) teaches mindfulness, distress tolerance, emotion regulation and interpersonal skills. It was developed by Marsha Linehan for people with intense emotions and has been adapted for many presentations. A meta-analysis of DBT in eating disorders, for example, found improvements in emotion regulation compared with control groups, though the number of studies was small.
- Cognitive behavioral therapy (CBT) helps people identify and change unhelpful appraisals and behaviors, and often includes gradual exposure to feared cues so avoidance no longer runs the show.
- Acceptance and commitment therapy (ACT) focuses on making room for difficult feelings while acting on personal values.
- Compassion-focused and schema-informed approaches target shame, self-criticism and long-standing relational patterns.
- Medication can help with co-occurring conditions such as depression, anxiety or sleep problems, and decisions about it should be made with a prescriber.
Choosing a therapist
Look for appropriate training and licensing in your country, experience with your concern, and a style that feels collaborative and respectful. Cultural fit and language matter. Many people find telehealth makes care more accessible, especially where in-person specialists are scarce. It is fine to ask a prospective therapist how they work with triggers and trauma, and to change therapists if it does not feel right.
9. Trigger Warnings and Avoidance: What the Evidence Shows
Trigger warnings and content notes are now common online, in classrooms and in media. They are usually offered with good intentions. The research on whether they reduce distress is less encouraging than many assume.
A 2023 meta-analysis in Clinical Psychological Science examined 12 studies. It found that warnings did not reduce distress after viewing sensitive content, did not meaningfully increase avoidance, and did not affect comprehension, but did increase anticipatory anxiety. The authors suggested that warnings tell people something upsetting is coming without telling them what to do about it, and that pairing warnings with emotion-regulation training might help.
How should we read this?
- Warnings may still serve other purposes, such as respect, transparency and giving people choice about what they engage with. The evidence concerns their effect on distress, not whether choice matters.
- Most of the research is experimental and short-term, and it cannot capture every real-world context or every clinical population.
- Avoidance has a cost. Avoiding every reminder can shrink life and reinforce fear over time. The longer-term goal in many therapies is not a life that never meets a trigger, but a life in which triggers can be met with skills and support.
- That does not mean forcing exposure. Gradual, planned and supported exposure works very differently from being overwhelmed unprepared.
A balanced approach is to give people honest information and real choice, and to pair it with practical tools and support.
10. For Professionals: Working With Triggers in Practice
Anchor in trauma-informed principles
SAMHSA’s framework offers a widely used structure: the four Rs (realize the widespread impact of trauma, recognize its signs, respond by integrating this knowledge, and resist re-traumatization) and six principles (safety; trustworthiness and transparency; peer support; collaboration and mutuality; empowerment, voice and choice; and attention to cultural, historical and gender issues). In practice, these translate into small, concrete behaviors: explaining what will happen in a session, offering choices, asking permission before moving into difficult material, and noticing how the environment itself may be activating.
Clinical pointers
- Normalize first. Psychoeducation about the alarm system, the window of tolerance and conditioning reduces shame and helps clients see reactions as understandable.
- Build a shared formulation. Map cue, interpretation, body response, emotion, behavior and consequence together. Include maintaining factors such as avoidance, safety behaviors and current stressors.
- Stabilize before you process. For clients with significant dysregulation, dissociation or unsafe coping, many models favor a phased approach: safety and skills first, trauma processing later. Phase-oriented care is a guide, not a rigid rule, and some clients do well with earlier processing.
- Teach a small toolkit. A few well-practiced skills (grounding, paced breathing or alternatives, labeling, a pause plan) are usually more useful than a long list.
- Pace within the window. Watch for signs of hyper- or hypoarousal in session, such as changes in voice, gaze, posture, breathing or responsiveness, and adjust. Close sessions with grounding and a brief check on safety and next steps.
- Address avoidance thoughtfully. Distinguish adaptive avoidance, which protects when resources are low, from avoidance that maintains impairment. Plan graded approaches collaboratively.
- Track between sessions. Brief logs, ratings and validated measures help see progress and refine the plan.
- Mind language. Clients may use “triggered” loosely. Ask what they mean and use their words where helpful.
Cultural humility
Triggers, expressions of distress and ideas about coping vary across cultures. Clients may describe reactions in bodily, spiritual or relational terms rather than psychological ones. Ask what the experience means to them, what healing looks like in their community, and what resources, such as family, elders or faith practices, are already available. Use qualified interpreters when language is a barrier, rather than relying on family members.
Looking after yourself
Working with distress can trigger clinicians too. Vicarious traumatization, compassion fatigue and countertransference are real. Regular supervision, peer consultation, boundaries and your own supports are part of ethical practice, not extras.
11. Supporting Someone Who Is Triggered
If someone you care about is having a strong reaction:
- Stay calm and slow. Your regulated presence helps more than the perfect words.
- Ask what helps. “Do you want company, space, or something to do with your hands?” gives them control.
- Keep language simple and concrete. Avoid long explanations or arguments in the moment.
- Don’t minimize or push. Avoid “just calm down” or “it’s not a big deal.” Also avoid forcing them to talk about what happened.
- Follow up later. Once things settle, ask whether they would like to talk and how you can help next time.
- Look after yourself. You are allowed to have limits and to encourage professional help.
12. A Global Perspective
Emotional triggers are universal, but the way people experience, describe and respond to them is shaped by culture, language, gender, religion, social context and the realities of their daily lives. Stigma remains a barrier in many places, and the WHO notes that most people with mental disorders do not have access to effective care. That makes accessible self-help and community support especially valuable.
Tools such as the WHO’s Doing What Matters in Times of Stress were designed for use by anyone, in any setting, with translations and audio exercises available in a number of languages. Community, family, faith and cultural practices can be valuable resources, and they work best alongside, not instead of, professional help when it is needed and available.
13. When to Get Help
Reach out to a doctor, therapist or other qualified professional if you notice:
- Reactions that are frequent, intense or long-lasting.
- Flashbacks, nightmares, or feeling that past events are happening now.
- Growing avoidance of people, places or activities that matter to you.
- Heavy reliance on alcohol, drugs, risky behavior or self-harm to cope.
- Persistent numbness, hopelessness, or difficulty functioning at work, school or home.
If you are in crisis or thinking about harming yourself or someone else, please seek help immediately. Contact your local emergency number, go to the nearest emergency service, or reach out to a crisis line. If you are unsure where to turn, findahelpline.com lists helplines by country. Examples include 988 (Suicide & Crisis Lifeline) in the United States and Samaritans on 116 123 in the UK and Ireland. If you are with someone in danger, stay with them and call emergency services.
14. Build Your Personal Trigger Plan
Copy these prompts into a notebook or notes app and fill them in when you are calm.
- My top three triggers are:
- My early warning signs (body, thoughts, behavior) are:
- The things that make me more vulnerable are: (sleep loss, hunger, conflict, loneliness, alcohol, workload)
- My first-step skill when I notice the signs: (name it, ground, slow breathing, step away)
- Three things that usually help me settle:
- Things I want to avoid doing when triggered:
- People I can contact, and what I will ask them for:
- A sentence I can say to others: (“I need ten minutes and I’ll come back to this.”)
- Professional or crisis contacts I will use if I need more help:
- How I will care for myself afterward:
Key Takeaways
- A trigger is a learned link between a cue and a strong reaction. It is understandable, not a flaw.
- Triggers push us outside our window of tolerance, either toward overwhelm or toward shutdown. Regulation means returning to, and gradually widening, that window.
- Name it, ground it, slow down and create space. These simple steps are backed by research and recommended in WHO self-help guidance.
- Suppression tends to backfire. Reappraisal, labeling, mindfulness and acceptance usually serve better, and they work best when practiced regularly.
- Avoiding all triggers is rarely a long-term solution, and warnings alone do not reduce distress. Skills and support do more.
- Trauma-focused CBT and EMDR are among the recommended treatments for PTSD. Many other therapies help with emotion regulation.
- Professionals can work safely with triggers through trauma-informed principles, shared formulation, pacing, skills teaching and cultural humility.
- If triggers are affecting your life, or if you are in crisis, reach out for help. You do not have to manage this alone.
References and Further Reading
- World Health Organization. Mental disorders (fact sheet). https://www.who.int/mediacentre/factsheets/fs396/en/
- World Health Organization (2020). Doing What Matters in Times of Stress: An Illustrated Guide. https://www.who.int/westernpacific/publications/i/item/9789240003927
- Substance Abuse and Mental Health Services Administration (2014). SAMHSA’s Concept of Trauma and Guidance for a Trauma-Informed Approach. Summary: https://youth.gov/feature-article/samhsas-concept-trauma-and-guidance-trauma-informed-approach
- Centers for Medicare & Medicaid Services. Applying the 4Rs: A trauma-informed approach in nursing facilities. https://www.cms.gov/files/document/coe-nf-apply-4rs-trauma-informed-approach-nursing-facilities-final-508.pdf
- Lieberman, M. D., et al. (2007). Putting feelings into words: Affect labeling disrupts amygdala activity in response to affective stimuli. Psychological Science, 18(5), 421–428. https://pubmed.ncbi.nlm.nih.gov/17576282/
- Gross, J. J. (2002). Emotion regulation: Affective, cognitive, and social consequences. Psychophysiology, 39(3), 281–291. https://pubmed.ncbi.nlm.nih.gov/12212647/
- Goyal, M., et al. (2014). Meditation programs for psychological stress and well-being: A systematic review and meta-analysis. JAMA Internal Medicine, 174(3), 357–368. https://pubmed.ncbi.nlm.nih.gov/24395196/
- Bridgland, V. M. E., Jones, P. J., & Bellet, B. W. (2023). A meta-analysis of the efficacy of trigger warnings, content warnings, and content notes. Clinical Psychological Science. Summary: https://www.psychologicalscience.org/news/2023-october-content-warnings-distress.html
- World Health Organization mhGAP guidelines for conditions related to stress (summary table). https://pmc.ncbi.nlm.nih.gov/articles/PMC4793547/table/Tab1
- World Health Organization (2023). mhGAP guideline for mental, neurological and substance use disorders (3rd ed.), recommendation record. https://bigg-rec.bvsalud.org/en/recommendations/d4176e766bf05aa400d7dd88a9a1e6102e8b6b0f
- Rozakou-Soumalia, N., Dârvariu, Ş., & Sjögren, J. M. (2021). Dialectical behaviour therapy improves emotion dysregulation mainly in binge eating disorder and bulimia nervosa: A systematic review and meta-analysis. Journal of Personalized Medicine, 11(9), 931. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8470932/
- Siegel, D. J. (1999). The Developing Mind. New York: Guilford Press. (Source of the “window of tolerance” concept.)
- Find A Helpline. https://findahelpline.com
Disclaimer: This article is provided for general information and education only and does not constitute medical, psychological or other professional advice. It does not create a professional relationship between you and The Good Mental Health Resources. Always consult a qualified health professional about your individual circumstances. If you are in an emergency, contact your local emergency services immediately.